Showing posts with label infection prevention and control. Show all posts

Saturday, 17 September 2016

MERS is a disease we spread...

There is little doubt now that Middle East respiratory syndrome  (MERS) disease outbreaks are triggered by sporadic zoonotic transmission of the MERS coronavirus (MERS-CoV) from an infected camel to a susceptible human. 

Little doubt to anyone who has followed the story of MERS at all, anyway.

But that's just the tip of the iceberg. 

The majority of human cases that have contributed to those steep rises in the cumulative MERS-CoV detection graph below are there because humans have infected other humans while in or associated with a healthcare facility. A telling picture when you consider that MERS-CoV is not a great transmitter. We've done much to make something from what should have been nothing.

Can we vaccinate against lapses in infection prevention and control?


Sunday, 4 September 2016

There (might be) something in the air tonight... [UPDATE]

UPDATE No.1 06SEPT2016
One of the early pieces of science-based news to come out of the May-2015 Middle East respiratory syndrome coronavirus (MERS-CoV) outbreak in South Korea was a June-2015 piece asking whether air conditioning may have played one (of many?) key role in facilitating the spread of virus from infectious patients, within healthcare facilities.[1]

In a publication that came out in April 2016 (yes, the literature did not see much detail on the South Korean outbreak for quite some time), authors described a study to collect and test air and swabs from surfaces in and outside patient's rooms, and their restrooms, in 2 hospitals that housed 3 male cases of MERS pneumonia.[2]

Whenever RT-PCR is used for this sort of work, it brings with it the question of whether infectious virus-containing droplets were captured, or only bits of non-infectious RNA viral genome was detected. This group, like those in the last post (who did not collect air samples), attempted to grow infectious virus. They could confirm that it was infectious virus by observing cell changes in infected laboratory cultures which were also RT-PCR positive. Also the same approach as that described by the South Korean study reviewed in the last post.[3] Additionally, the infected cell cultures also reacted to an anti-Spike protein antibody in a fluorescent test and they even saw some actual virus from swab cultures (not captured air samples?) using electron microscopy.

Some interesting findings from the use of these test on air and swabs samples included:

  • All air samples from both hospitals were RT-PCR positive and these included the detection of MERS-CoV of RNA in room, restroom and common corridor air. Infectious virus was grown in cells from from 4 of 7 (57%) samples.
  • 42 of 68 (62%) surface swab samples tested positive for MERS-CoV RNA by RT-PCR and included elevator button and rails, doorknobs and handrails inside and outside a patient's room, telephone button, toilet seat, call button, patient pillow, nasal prong, toilet seat, TV, keyboard, stethoscope and air exhaust dampers. Infectious MERS-CoV was isolated from 15 swabs of some of these items including an elevator button, nasal prong, patient pillow, TV, bed handrail, keyboard, stethoscope, toilet seat and an air exhaust damper

This study really addresses three big issues. 

Firstly MERS-CoV from very ill patients late in their disease course, thoroughly contaminates a hospital room and its surrounds - not just with detectable genetic material, but with infectious, viable MERS-CoV virus. 

Secondly, surface contamination was detected from swabs collected 3-7 hours after daily room cleaning suggesting either that cleaning was insufficient or that new virus was quickly laid down on cleaned surfaces (with no lasting anti-viral effect from the cleaning solution). 

Thirdly, the capture of infectious virus from the air implies that the virus maybe present in droplets or droplet nuclei with implications for the level of personal protective equipment required for healthcare workers and visitors to an infected person bedside. It also pertains to the distance away from a case that is considered "safe" for an uninfected person to be. Six feet may not be nearly enough distance, at least if that is a prolonged period in a room.

This provides some more data to explain how MERS-CoV may be associated with hospital outbreaks. Why it has been allowed to get away with this is a matter for infection prevention and control specialists in each and every healthcare facility to address.

UPDATE.

After this was published, Van Kerkhove and colleagues wrote a letter to the editor to make some points about the study noting:

  • an absence of negative control sampling from areas where MERS-CoV patients were not housed.
    Absolutely. I'd even suggest a few different sites in very distant hospital areas from where MERS patients were housed, given the possible human-spread of virus around a facility during and the possibility of silent or subclinical infection in patients admitted to hospitals for other reasons during times of outbreak. This will explore whether false positive laboratory results are occurring.
  • other studies have reported surface contamination that did not yield viable virus. Van Kerkhove note that these negative findings need to be published to balance the literature. Always.
    However, it's well known that virus culture is insensitive compared to RT-PCR methods so it
    may fail to detect infectious virus which may be enough to infect a human . It may also be that infectious virus capable of infecting another person who comes into contact with it is not always present in the air or on surfaces. It may be that the surfaces often simply have non-infectious "bits" of virus detected by RT-PCR -these cannot cause a new infection. But in this study infectious virus was able to be isolated from air and surfaces...unless Van Kerkhove and colleagues are implying contamination of the cultures in some way.
  • the need to replicate these findings in other studies.
    Always.
    But as is often the case, let's not wait on those findings to recognise that infectious droplets and contaminated surfaces now have some more data to support them and that they fit nicely into a picture of hospital transmission. Precautionary principle.
A second letter was also written by Myoung-don Oh,[7] noting:


  • few infected cells in the cultures / slow growth.
    This isn't too surprising, it may just reflect that there was a low amount of virus in the air, added to the cell cultures compared to that used from the control virus (cell adapted?) stock.
    This may mean that the risk from airborne transmission in these rooms is low. However, since we don't know what amount of MERS-CoV is required to start a new human infection, this is a moot point.
  • the sequences of the room samples were too different from each other.
    This is a bit surprising since within an outbreak, MERS-CoV doesn't usually vary much at all. I'll have a look at how much South Korea's MERS-CoV Spike gene sequences varied and come back to this point.

Both letters were replied to.[8]

References...


  1. Did poor ventilation lead to MERS 'superspread' in Korea?
    http://www.sciencemag.org/news/2015/06/did-poor-ventilation-lead-mers-superspread-korea
  2. Extensive Viable Middle East Respiratory Syndrome (MERS) Coronavirus Contamination in Air and Surrounding Environment in MERS Isolation Wards
    http://cid.oxfordjournals.org/content/early/2016/06/08/cid.ciw239.abstract
  3. Korea contamination: Middle East respiratory syndrome coronavirus in the room..
    http://virologydownunder.blogspot.com.au/2016/09/korea-contamination-middle-east.html
  4. Interpreting Results From Environmental Contamination Studies of Middle East Respiratory Syndrome Coronavirus
    http://cid.oxfordjournals.org/content/early/2016/08/09/cid.ciw478.full.pdf
  5. STABILITY OF MIDDLE EAST RESPIRATORY SYNDROME CORONAVIRUS (MERS-COV) UNDER DIFFERENT ENVIRONMENTAL CONDITIONS
    http://www.eurosurveillance.org/ViewArticle.aspx?ArticleId=20590
  6. Transmissibility of Middle East Respiratory Syndrome by the Airborne Route
    http://cid.oxfordjournals.org/content/early/2016/08/09/cid.ciw479.full.pdf
  7. Interpreting Results From Environmental Contamination Studies of Middle East Respiratory Syndrome Coronavirus
    http://cid.oxfordjournals.org/content/early/2016/08/09/cid.ciw478.full.pdf
  8. Reply to Kerkhove et al and Oh
    http://cid.oxfordjournals.org/content/early/2016/08/09/cid.ciw480.extract
Update...
  1. Added in detail on letter by Van Kerkhove and colleagues [4], and rebuttal authors [5]

Friday, 2 September 2016

Korea contamination: Middle East respiratory syndrome coronavirus in the room..

This post has been moved to the new Virology Down Under platform on WordPress.

You can get to this specific post by clicking on the link below...


Please adjust your bookmarks.

Apologies for any inconvenience.

Saturday, 5 December 2015

The season of the MERS...is mainly whenever the infection control fails

I still only see a "seasonality" to MERS and human MERS-CoV detections that is made up of the times when hospital outbreaks spread cases due to missed opportunity to control and prevent infection wihtin their walls. In other words - no real season at all. 

MERS-CoV is an opportunistic virus - which includes making the most of the frequent opportunities we humans provide for it to spread.

Data from public sources up until December 3rd 2015.
Click on image to enlarge.

Any true seasonality is in that small percentage of cases that are the result of a primary, sporadic infection from an infected and infectious camel. Those cases may be related to times of camel calf weaning when young camels acquire their first infection, or it might just be whenever a particular herd has MERS-CoV raging though it.


MERS-CoV: Saudi Arabia still tops the chart..by a long way

A quick reminder that MERS and the MERS-CoV remain a thing of the Kingdom of Saudi Arabia from where 80% of detections have been reported.

South Korea's hospital outbreak comprises 11% of all reported detections.


Thursday, 10 September 2015

Ignore mild and asymptomatic cases at your peril...

Infected but apparently well people may be key points along the transmission chain - not just in spreading infectious virus, but also in contaminating surfaces.

Or they may have no role in transmission at all.

When you have problems that weren't solved by the easy answers - look harder.

Study. Test. Find out. Communicate.
Knowing the full story of how a virus spreads is hard work. But transmission is not necessarily a simple process. Like everything biological, it may be more complex than we care to acknowledge. Such a complex scenario is shown here. Completely fictitious.
Or maybe not.
Testing can answer questions. Communication can provide answers.
Click on image to enlarge.

Tuesday, 27 January 2015

Societal change and H7N9..

The importance of societal change for controlling infectious disease outbreaks really cannot be over-stated. 

For Ebola virus disease, it came down to stopping the tradition of direct contact with the body of those who have died and dircet contact in general. For MERS it
seems that occasional camel contact triggers insertion of the MERS-CoV virus into hospitals where lax infection prevention and control practices add to the case load. 

For influenza A(H7N9) virus cases, it is the habit of obtaining live poultry from retail markets where rare virus-laden chooks are culled and handed over because of a desire to see, choose and purchase the tastiest fresh chicken. 

There is a common thread among these stories about direct contact or inefficiently droplet-transmitting virus infections: we can stop their spread. 

But we also amplify and prolong their spread. 

However, when it comes to human-adapted, efficient droplet-spread or airborne-transmitted viruses - well, then we're in trouble. Of course we could all just lock ourselves in a room for a few weeks but that won't ever happen.

So its very important to head off these "emerging" viruses while we still have a modicum of control over them. Once they get away from that control, and theoretically that could happen in the blink of an eye-right now even-no amount of fancy infra red cameras, poorly donned surgical masks or fancy hospitals laden with machines that blink and go ping, will stop them from spreading globally.

Cheery.

In the meantime - here's hoping China speeds up the closure of those live poultry markets. Habits can be changed but death is forever.

Click on image to enlarge.

Monday, 22 September 2014

Ebola virus, HCWs infections and personal protective equipment..

No one could offer anything but our deepest and most heartfelt thanks and a feeling of pride in the selfless, essential and humanitarian work being done by healthcare workers (HCWs), both local and international, in West Africa.

But they have paid a high price for this work, as they always do in emerging disease outbreaks.


WHO Ebola virus disease
numbers up to
14-Sept-2014
Of the >5,300 people reported as infected by the West African variant of Zaire ebolavirus (EBOV) to date, around 315 have been HCWs. Both numbers are very likely an underestimate. Half of the HCW cases have died. I don't know just how many HCWs there are in Guinea, Liberia and Sierra Leone who are dealing with the EBOV outbreak. I do know that these deaths are as horrible as each of the losses among non-HCWs, and are also worrying for those trying to recruit the many more HCWs needed to expandthe  care of ill patients.


This week a commentary article on the Centre for Infectious Disease Research and Policy (CIDRAP) website delves into this issue by suggesting an improvement to HCW respiratory protection.[1]


Two quick things first:

  1. The World Health Organization (WHO) defines human transmission of Ebola virus as being by direct contact (between mucous membranes or a break in the skin and the blood and other body fluids of an infected individual via physical contact or by wet material being propelling onto mucous membranes or skin breaks) and by indirect contact via contaminated surfaces.[3,4]
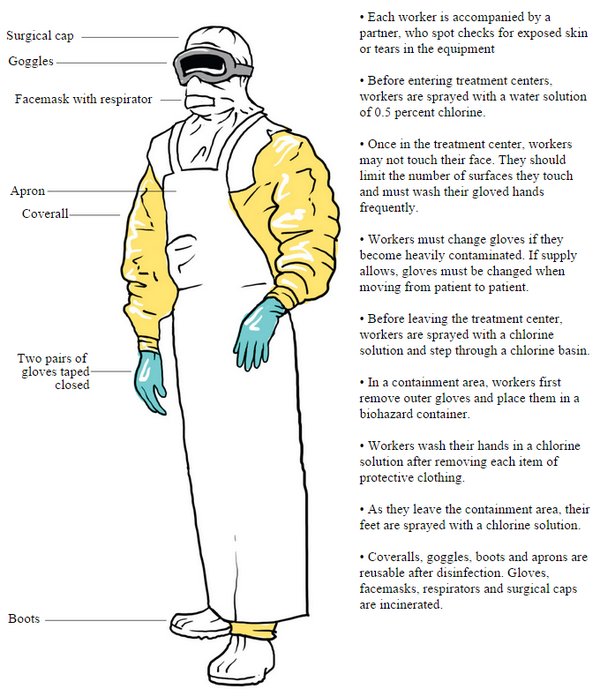
  2. When dealing with patients, the WHO recommends wearing gloves, a disposable impermeable gown to cover exposed skin, a waterproof apron over any gown that is not impermeable or when undertaking strenuous activity, facial protection to prevent splashes to the nose, mouth and eyes including a medical mask + eye protection (visor or goggles) or a face shield and medical mask.[3]
The CIDRAP article's authors claimed a belief that there is scientific and epidemiologic evidence that Ebola virus has the potential to be transmitted via infectious particles. Unfortunately they don't make a convincing argument to support their belief-nor could they, since no data currently exist to for any claim that an Ebola virus is transmitted between humans by an airborne route. So we're left with a commentary based on those beliefs, and some speculation.

Some collaborators and I wrote about Ebola virus not being an airborne virus based on what I know and what's been done to answer this question before.[2] I'll first add that if it were an airborne virus, I would likely be seeing many, many more cases-"Compared to this Ebola outbreak, the H1N1 swine flu had already spread to an estimated 10,000 times as many people in its first 10 months" noted United Kingdom virologist Ben Neuman.[13] H1N1 being an influenza A virus; a real airborne virus. In our post, we noted that big wet droplets (part of an "aerosol"-a messy term that may not be well understood by the public...or some scientists...that includes big wet droplets and the more frequent smaller particles <100µM in diameter) can be propelled at a mucous membrane or fall to the ground to contaminate surfaces.


A schematic of the makeup of an "aerosol".
From [2]
Big wet, propelled droplets can contain infectious Ebola virus and are included in the established risk messaging. Hence the need for droplet precautions.

We also know that from every human aerosol, after the heavy larger droplets fall to the ground or impact on a surface, the many more remaining lighter particles can linger in the air. I know that these small <100µm particles can be made to contain infectious Ebola virus under lab conditions[8] thus droplet nuclei produced by an infected human may contain Ebola virus. I can't say with certainty that they do or do not. However, as far as I have been able to tell, infection of humans and resultant disease from inhaling lingering particles, has not occurred. And when an airborne route was investigated using infected and uninfected non-human primates housed nearby but without direct contact, no infection via an airborne route was found to have taken place.[9]


Most of the studies looking at aerosols of Ebola virus do so in highly temperature and humidity-controlled laboratories with lots of lab-grown virus.


Relying on one added component raises a few questions for us:

  • Could the faith in this one extra precaution threaten the very important, meticulous care required when donning, using, and removing contaminated PPE-of any sort?
  • What role does a lack of the basics, like soap and clean water [10], play in HCW infections?
  • Could an additional extra safety measure really have a major effect on reducing the known risks involved with treating Ebola virus disease (EVD) patients, such as the long hours, tiredness, the constant and pervasive tension of imminent exposure, the oppressive heat, delirious and sometimes violent patients and the ease with which one can self-inoculate?[6]
  • Does the extra safety measure even have a role in reducing risk associated with HCWs who are unknowingly infected while not wearing PPE?[7]
How much do the things listed above, mostly unrelated to having a hi-tech battery-powered breathing apparatus on your hip, contribute to the tally of HCW infections?

The authors overlooked mentioning that early on, many HCWs may have had few or no masks at all and few other essential barriers such as those listed by WHO above, to protect against direct contact. They also did not mention the lack of HCW training in the use of any of that equipment if available, and did not highlight the lack of experience HCWs had dealing with EVD patients. These HCWs had (and may well still have) direct contact with very ill EVD cases, and got infected. What fraction of HCW infections resulted from absent or incomplete PPE and training versus the HCWs that they believe became ill while wearing full droplet precaution PPE?


Embedded image permalink
MSF designed suit of PPE.
Graphic tweeted by the
Washington Post.[5]
Others have also made note of the disparities between the imagery of a biosafety level 4 (BSL4) laboratory researcher working in a negatively pressurized, airlocked laboratory within a tethered, airtight suit (probably unnecessarily high precautions [13]) versus highly biocontained single patients being shipped home on dedicated planes (kept somewhat contamination-free using isolators) to rich nations for specialized support and treatment versus Médecins Sans Frontières (MSF) workers who use respirators (specialized face masks that fit more snugly and contain more layers to better filter what is breathed in) instead of surgical masks versus the WHO recommendations of standard precautions which include a surgical mask. Notably, the WHO recommendations vary according to the type of risk one is exposed to [see pg 96-7 96 of the 113 pg PDF at [3]).[10] There clearly is a range of thinking and messages here. But equally, there are a lot of different applications to cover, and no way for every need to be specifically catered for by one guideline. If everyone could agree on such a thing anyway.

I share the concern of many over the deaths of HCWs in West Africa. They may still be unnecessarily exposed to the virus due to the lack of enough PPE. They may not have enough training to understand how easy it is to become infected. They may not be given the message that during an EVD outbreak as monstrous and different as this one, many heavily populated areas have been included for the first time resulting in very real risks of infection occurring outside the hospital setting, not just inside it. There are also real risks of infection in supposedly EVD-free hospital settings like maternity wards.[11] There are many, many non-airborne related risks for HCWs.


We freely admit that we are not trained in the use of PPE for treating Ebola patients; just for working with actual respiratory and blood-borne viruses in PC2 & PC3 laboratory settings, respectively. Still, some may find this post irrelevant.
This is a blog and not part of any Organization's reference list when they write PPE guidelines...because it's a blog.

But for what it's worth, I would follow the MSF lead if working on the battlefield of a 100+ bed treatment facility. In an ideal world, more effort would be made to provide a more roomy and breezy head covering that allows patients to see your face and which can be worn for longer periods would be useful. You can see an image provided by 3M of this battery-powered air-purifying respirator (PAPR) accompanying the CIDRAP post.


However....first and foremost, and well before we get to this level of hair-splitting based on speculation and belief and no evidence of an airborne virus-I'd be wanting to make sure there was a minimum level of disposable PPE actually available for use, that it was consistently used by every HCW, that appropriate training in its use had been provided, and that HCWs understood about all the risks for acquiring EBOV infection. 

Reasons for HCW infections are many and varied. As much as we may believe or wish it were so, no single act or change will circumvent these risks or these infections.


References..

Saturday, 24 May 2014

MERS-CoV among healthcare workers: no longer identified or the end of a hospital cluster?

Just looking at @maiamajumder's vast array of MERS-related charts on Twitter and had a thought.

She and I and others have been wondering for a while if perhaps the Kingdom of Saudi Arabia's (KSA) Ministry of Health (MOH) reporting has decided to simply no longer identify healthcare workers (HCWs) as such. That would not be the strangest thing to occur with these data, believe me (deaths that have been "previously reported" that actually haven't, people who were discharged from hospital who were previously not described as being hospitalised, and of course, some instances of HCWs in KSA being identified as MERS-CoV positive by their country of origin and not by the KSA MOH). Perhaps not identifying HCWs is a way of attempting to stop pointing to what was a huge problem in infection prevention and control just last month?

But perhaps that is not entirely what is happening. 

Perhaps there is another reason and there may be some precedent to support it; HCW numbers have in fact realistically decreased because they are no longer being infected as often. Why not? Perhaps because April's Jeddah hospital-based MERS-CoV outbreak is under control. Have a look at the chart below. Some things to note afterwards:


Click on image to enlarge
  1. HCW numbers have stopped accumulating so rapidly. That mirrors total MERS-CoV detections of course. See some recent posts on the now receding wave of April's MERS surge here and here.
  2. The precedent I mentioned? When the Al-Ahsa hospital-related outbreak stopped in May 2013, so did the number of HCW positives/week dropped away. 
  3. There have clearly been a bunch of other HCW peaks which may also have been related to hospital-clusters that were not so obviously publicised (I'll have a loo over this some time in the future). Those spikes of HCW infections have narrower bases and higher peaks than does the Jeddah outbreak, so perhaps that can be used as an indication of them being short-lived clusters that were better controlled than Jeddah. Not rocket science I guess and probably stating the obvious to the experts out there.
  4. Infections in HCWs serve, as we already know, as a kind of sentinel system for identifying a spike in overall cases since more severe disease shows its face in hospitals and most likely represents the presence of other cases out in the community. His statement is much more believable now that we ;can look back and know that milder signs and symptoms of disease, or none at all, do not infrequently follow MERS-CoV infection).
I hope that our original hypotheses - that the KSA MOH has quashed identifying HCWs - was wrong. Heading towards Hajj-2014, it would be best to be polishing the very tarnished reputation of of the KSA MOH on matters ;of communication, not further damaging it.


Sunday, 29 December 2013

What to watch for with human parechovirus (HPeV) infections...

This post has been moved to the new Virology Down Under platform on Wordpress.

You can get to this specific post by clicking on the link below...
 

Please adjust your bookmarks.

Apologies for any inconvenience.

Friday, 1 November 2013

Infection prevention and control and MERS

Harriman, Brosseau and Triverdi have written to the Editor of the New England Journal of Medicine (NEJM) to express their concerns over the lack of apparent preventative measures undertaken during the Al-Ahsa Middle East respiratory syndrome (MERS) coronavirus outbreak communicated by Assiri et al (previously reviewed here).

The new letter indicates that with so little known about MERS-CoV transmission route(s), a safer bet would have been to protect healthcare workers as much as possible. They suggest use of  respirators rather than surgical masks (see Mike Coston's reviews of the differences here, here, here, here and here...likes his masks does Mike). 

Possibly eye protection as well given the transmission unknowns. 

I've previously listed these and other precautions for managing patients with endemic or with less well-defined respiratory pathogens. Worth a reminder read.

The authors highlight it would be prudent, in a well-resourced country like the Kingdom of Saudi Arabia, to roll out as many extra personal protective safeguards for the front-line healthcare workers as possible; at least while the slow hunt to understand how the virus is acquired and transmitted seeks some answers.

The reply to this letter by Memish, Al-Tawfiq and Assiri did not specifically agree with its specifics or address enhanced care for HCWs, instead restating what was done to respond. The key comment summing up the use of respirators indicates a reactive rather than proactive approach to HCW care in trying to prevent a case from spreading their laboratory confirmed infection. 

...putting surgical masks on all patients undergoing hemodialysis and particulate respirators (N95 masks) on any patient with confirmed MERS-CoV who was undergoing an aerosol-generating procedure...

As we've seen over and over again during this outbreak and others, by the time a laboratory confirmation is available, it is far too late to halt early transmission events. 

When those events occur in a hospital environment it's not just the relatively (to the MERS-CoV case averages) younger and more healthy HCWs that are at risk of infection and disease. MERS-CoV and other respiratory viruses are at their most lethal among the elderly with comorbidities. Delays in lab testing, in waiting for something to happen or in following other's guidelines to the letter rather than modifying or creating new ones based on front-line experiences, can have severe consequences.

I take the message from this letter as: Be proactive not reactive.

Friday, 18 October 2013

Middle East coronavirus infection control and personal protective equipment...

...are not at all part of the thinking judging by the imagery in this story on alRiyadh.

For a virus that kills 2 in 5 symptomatic people and for which animal hosts or intermediate hosts remain to be excluded or confirmed, there is an alarming and completely irresponsible level of safety being employed by those workers.

Thanks to FluTrackers for bringing it to my attention.

Thursday, 8 August 2013

Infection Prevention and Control measures for MERS..mostly as per other ARIs

Thanks to Mike Coston for help and tips.

Cases are few and details are incomplete but the authors of an article in the recent MERS-centric issue of the EMRO Journal, recommend following the basic protocols you would to suppress spread of any virus capable of causing an acute respiratory infection (ARI) with a leaning towards those that worked well to interrupt hospital-based spread of severe acute respiratory syndrome (SARS) coronavirus.

Some key points from the paper, of highest relevance to our current knowledge of the  MERS-CoV are  listed include (not in specific order or priority):

  1. Identify patients with ARIs and prevent them from transmisttign the agent to helathcare worklers and patients
  2. Droplet and contact precautions for people with ARIs
  3. Separate ARI patients by ≥1m from other patients and from HCWs
  4. Use personal protective equipment (PPE) including eye protection, gloves, long-sleeved gowns and surgical mask/procedure mask/particulate respirator if aerosol-generating procedures are to be performed (tracheal intubation alone or with cardiopulmonary resuscitation or bronchoscopy being notable risks)
Mike Coston's description of the mask debate is very helpful for #4 above.

If a particular infectious diagnosis can be made, then patients with that diagnosis, say MERS-CoV,  can be cohorted - co-located to minimize spread to uninfected patients and maximise specialised care and efficient use of available resources.

Specifically, the article includes a list of SARS-like IPC precautions listed include which may be useful for known MERS-CoV infections. Many of these apply to ARIs due to endemic respiratory viruses and novel influenza viruses in general though:

  • Good hand hygiene
  • Use of PPE (gloves, gown, eye protection and medical masks for HCWs, caregivers and the patient if oputside their room
  • Particulate respirator for aerosol generating procedures
  • Separate, adequately ventilated room
While the above is written for dealing with infection in a healthcare setting, the WHO have also just released a rapid advice document for those caring for mildly ill MERS-CoV-infected people without underlying conditions, or those recently discharged from hospital. A mashup of 16 distinct points (read the document to see the full language and exceptions) home IPC are:

  • Limit contact with the ill person - maintain distance (perhaps limit exposure time?). 
  • Do not allow people at increased risk to care for the ill person
  • Hand hygiene and respiratory hygiene are important as are appropriate (soap and water, bl;each as recommended) cleaning of all surfaces in contact with the person or their secretions - kitchen, bathroom, toilet, bedframe, bedside tables, furniture etc
  • Discard contaminated tissues, masks etc
  • Clean clothes
  • Do not share eating utensils food or drionk, towels or bed linen
  • Caregiver to wear a mask - discard after use and do not handle while in use
  • Ventilate shared spaces

Close medical supervision is recommended for symptomatic or probable MERS cases and their contacts.

The WHO home care advice also notes lack of evidence for transmission of MERS (the disease) from asymptomatic, pre-symptomatic or early-symptomatic people. Thus quarantine or isolation of asymptomatic cases is currently unnecessary but possibly exposed people should monitor their health for 14-days.


Key documents and official websites to be familiar with: